Just a friendly reminder….
Headaches are REALLY common! In fact, two out of three children will have a headache by the time they are fifteen years old, and more than 90% of adults will experience a headache at some point in their life. It appears safe to say that almost ALL of us will have firsthand knowledge of what a headache is like sooner or later!
Certain types of headaches run in families (due to genetics), and headaches can occur during different stages of life. Some have a consistent pattern, while others do not. To make this even more complicated, it’s not uncommon to have more than one type of headache at the same time!
Headaches can vary in frequency and intensity, as some people can have several headaches in one day that come and go, while others have multiple headaches per month or maybe only one or two a year. Headaches may be continuous and last for days or weeks and may or may not fluctuate in intensity.
For some, lying down in a dark, quiet room is a must. For others, life can continue on like normal. Headaches are a major reason for missed work or school days as well as for doctor visits. The “cost” of headaches is enormous—running into the billions of dollars per year in the United States (US) in both direct costs and productivity losses. Indirect costs such as the potential future costs in children with headaches who miss school and the associated interference with their academic progress are much more difficult to calculate.
There are MANY types of headaches, which are classified into types. With each type, there is a different cause or group of causes. For example, migraine headaches, which affect about 12% of the US population (both children and adults), are vascular in nature—where the blood vessels dilate or enlarge and irritate nerve-sensitive tissues inside the head. This usually results in throbbing, pulsating pain often on one side of the head and can include nausea and/or vomiting. Some migraine sufferers have an “aura” such as a flashing or bright light that occurs within 10-15 minutes prior to the onset while other migraine sufferers do not have an aura.
The tension-type headache is the most common type and as the name implies, is triggered by stress or some type of tension. The intensity ranges between mild and severe, usually on both sides of the head and often begin during adolescence and peak around age 30, affecting women slightly more than men. These can be episodic (come and go, ten to fifteen times a month, lasting 30 min. to several days) or chronic (more than fifteen times a month over a three-month period).
There are many other types of headaches that may be primary or secondary—when caused by an underlying illness or condition. The GOOD news is chiropractic care is often extremely helpful in managing headaches of all varieties and should be included in the healthcare team when management requires a multidisciplinary treatment approach.
Most of know someone who has been affected by headaches. If they are looking for help and information please feel free to contact us at 204-586-8424 or at info@aberdeenchiropractic.com.
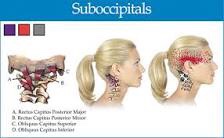
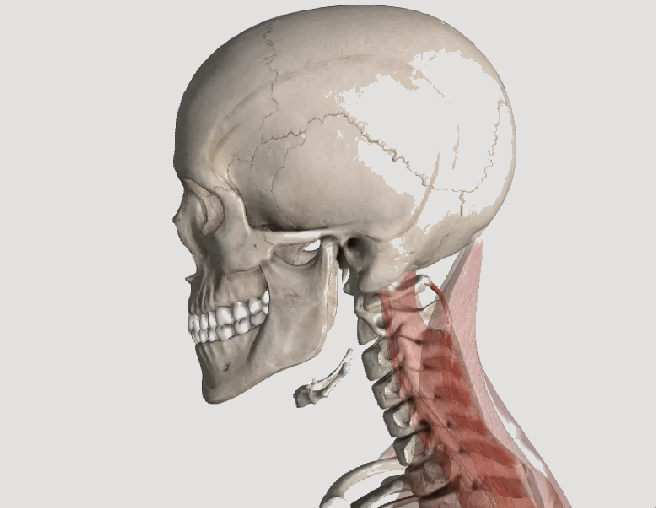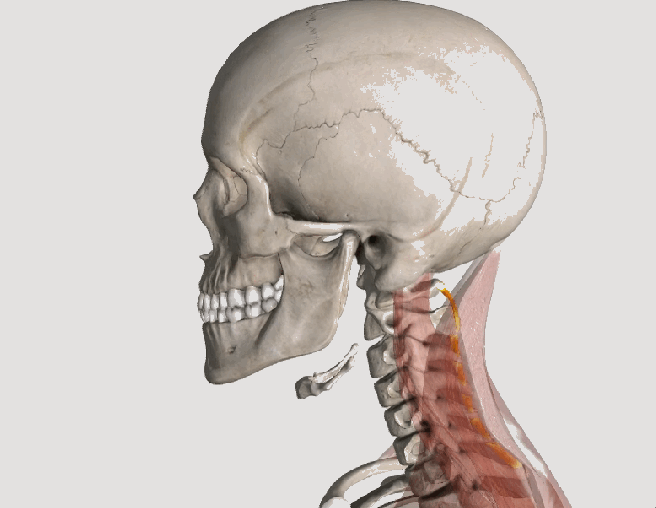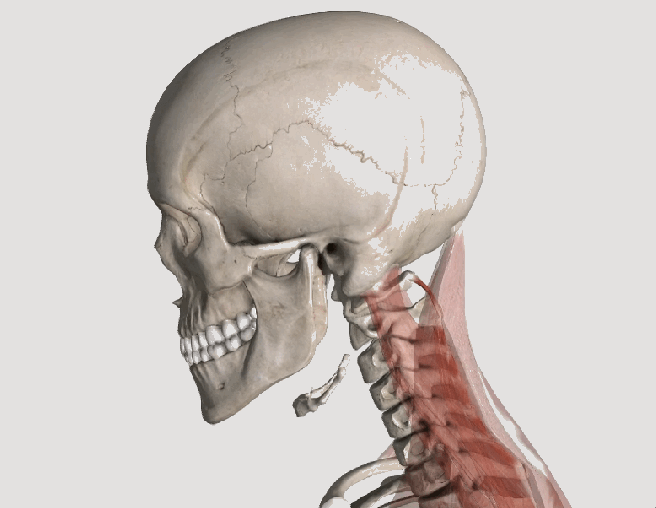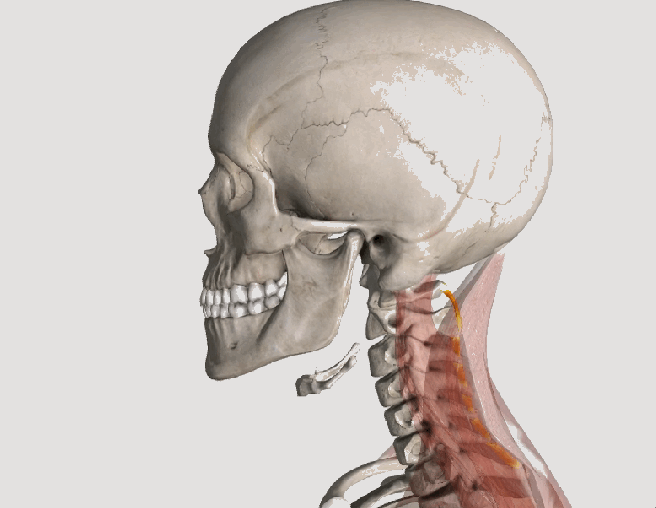
The suboccipitals are a group or four muscles that attach to the transverse and spinous process of C1 and C2 and the occipital bone.
These muscles provide extension side bending and rotation movements between the occiput and C1 and C2. These muscles are often overloaded due to postural strain. A classic example being sitting in front of a computer all day.
When these muscles are overloaded trigger points can develop. Pain and symptoms of trigger points in the suboccipitals include head pain that penetrates into the skull but is difficult to localize.
Patients are likely to describe the pain as “all over” including the occiput, eye and forehead, but without any clarity. Trigger points in these muscles are often associated with tension head aches
.

Over the next few weeks we will be addressing some common food myths that, frankly, drive us a little bit crazy when we hear them. Hopefully we are able to clarify some common misconceptions regarding diet and how what you eat affects how you feel and perform.
We are always open to discussion and want to hear any food myths you have heard in your travels that made you go “What?”.
So, without further delay, food myth #1:
Eating Fats Is Unhealthy
Generations of now adults have been brainwashed into believing that fats = getting fat by the Canada Food Guide. This is simply not the case. While some fats are unhealthy, plenty more have benefits that you won’t find elsewhere. A lower calorie eating plan that includes healthy fats can help people lose more weight than a similar diet that’s low in fat, according to a study in the International Journal of Obesity. Fats make food taste better, keep you fuller and help prevent overeating.
It is true that fats have more calories per gram than proteins and carbs but those calories come with health benefits that the others don’t. Healthy fats like the ones found in salmon, olive oil, nuts and avocados are key to several healthy living goals including:
1. They are a major fuel source for your body (meaning they provides a lot of calories) and are also the main way you store energy.
2. You need fat to help you absorb certain nutrients, such as fat-soluble vitamins (vitamins A, D, E and K) and antioxidants (like lycopene and beta-carotene).
3. Fats are important in giving your cells structure.
4. Omega-3 fats, a type of unsaturated fat, are important for optimum nerve, brain and heart function.
One type of fat you don’t need? Trans fats, an artificial kind of fat found in partially hydrogenated oils and a main ingredient in the food frying process (delicious, yes, but very unhealthy).
So there you go, a quick overview of why fats are important in every healthy diet. Come back next week for more food myth-busting.


Are there differences in lifestyle between people with vs. without fibromyalgia (FM)?
A recent study found women with FM found spend more time engaged in sedentary behaviors and less time in physical activity. In the study, researchers followed 413 female patients with FM and 188 age-matched healthy female controls. Researchers used three different approaches to access physical activity: a triaxial accelerometer to examine sedentary time, time spent in physical activity, and step counts.
They discovered those who suffered from FM spent an average of 39 more minutes per day in sedentary activity and 21 fewer minutes per day in light physical activity, 17 fewer minutes per day in moderate physical activity, and 19 fewer minutes per day in moderate-to-vigorous physical activity. In addition, those with FM took a mean of 1,881 fewer steps that those without FM.
Now, this isn’t really a surprise given the fact that people with FM are in pain and more likely to have difficulties sleeping and tolerating prolonged activities. After comparing the sufferers to the non-sufferers, the researchers found only 21% of FM patients vs. 46% of non-FM controls achieved the recommended 150 minutes/week (a little over 20 min. / day) of “moderate-to-vigorous” physical activity. They also found that only 16% vs. 45%, respectively, walked the recommended ≥10,000 steps per day.
One of the BEST forms of exercise for most people is walking. A walking program should be a staple exercise. It’s important to note that this should be GRADUALLY introduced so as to avoid an overuse injury—strain or sprain of the muscles and joints. This gradual introduction into activity is ESPECIALLY important for the FM sufferer as overuse injuries can make them afraid to do something that can REALLY help when done correctly!
Last week, we discussed some startling new research that found that lightheadedness upon standing up (orthostatic hypotension) may be more serious than previously thought. This month, we’ll look specifically at headache AND dizziness and if we should we be concerned about this combination of complaints and if so, when?
A team of researchers from Johns Hopkins University reviewed past medical records of 187,188 patients presenting to over 1,000 emergency departments (EDs) between 2008 and 2009. They found the combination of headache and dizziness—especially in women, minorities, and young patients—was a potential signal of an impending stroke!
Specifically, they reported that 12.7% of people complaining of headache and dizziness were later admitted for stroke and had been misdiagnosed and inappropriately sent home from the ED within the previous 30 days. Patients were told they had a “benign condition” such as inner ear infection or migraine, and in some cases, they weren’t given a diagnosis at all. Slightly less than half of this population had a stroke within seven days and over half had a stoke within the first 48 hours of the initial pre-stroke ED presentation!
The study reported that women were 33% and minorities 20-30% more likely to be misdiagnosed, suggesting gender and racial disparities may play a role. The researchers estimate that doctors miss 15,000 to 165,000 strokes that result in harm to the patient each year.
Studies have found that the early diagnosis and quick treatment of strokes is critical in reducing serious residuals in patients having a transient ischemic attach (TIA), sometimes referred to as a “mini-stroke” or “pre-stroke.” TIAs are often pre-cursors to a more catastrophic stroke leading to death or permanent disability without appropriate treatment.
Again, to put this in perspective, MANY people present to healthcare providers with headaches and dizziness with NO relationship to stroke—about 87%—though it is sometimes not possible to know whether a potentially dangerous problem may arise in the near future. The good news is that it usually does not!
The importance of this study is to alert both healthcare providers AND patients of the potential risk. When in doubt, it’s ALWAYS best to seek out multiple opinions. An MRI may be the best way to confirm the most common type of stroke (according the study reviewed above), as a CT scan may not show the brain changes early on and could lead to false reassurance.

The sternocleidomastoid muscle or “scm” is a strap like muscle located in the front of the neck. It originates on the manubrium of the sternum and the medial clavicle, and inserts on the mastoid process of the temporal bone( the lump or bone behind the ear). When working together the scm flexes the head and neck. The actions of one muscle working by itself is to rotate the face to the opposite side and lift it toward the ceiling.
Trigger points in this muscle usually form due to acute injury or to chronic postural stress. These trigger points can cause a wide variety of symptoms including pain felt in the cheek, temple, forehead, top of the head, and base of the skull. Trigger points in these muscles can also refer deep into the ear and cause postural dizziness.

Fibromyalgia (FM) is a very common, chronic condition where the patient describes “widespread pain” not limited to one area of the body. Hence, when addressing exercises for FM, one must consider the whole body. Perhaps one of the most important to consider is the squat.
If you think about it, we must squat every time we sit down, stand up, get in/out of our car, and in/out of bed. Even climbing and descending steps results in a squat-lunge type of movement.
The problem with squatting is that we frequently lose (or misuse) the proper way to do this when we’re in pain as the pain forces us to compensate, which can cause us to develop faulty movement patterns that can irritate our ankles, knees, hips, and spine (particularly the low back). In fact, performing a squatting exercise properly will strengthen the hips, which will help protect the spine, and also strengthens the glutel muscles, which can help you perform all the daily activities mentioned above.
The “BEST” type of squat is the free-standing squat. This is done by bending the ankles, knees, and hips while keeping a curve in the low back. The latter is accomplished by “…sticking the butt out” during the squat.
Do NOT allow the knees to drift beyond your toes! If you notice sounds coming from your knees they can be ignored IF they are not accompanied by pain. If you do have pain, try moving the foot of the painful knee about six inches (~15 cm) ahead of the other and don’t squat as far down. Move within “reasonable boundaries of pain” by staying away from positions that reproduce sharp, lancinating pain that lingers upon completion.
Posture assessment is a key component of the chiropractic examination, and the posture of the head and neck is especially important for a patient recovering from a whiplash injury. Forward head carriage describes a state in which the head sits more forward on the shoulders than it should. In order for the muscles in the neck and shoulders to keep the head upright, they must work harder. This added strain can increase one’s risk for neck pain and headaches, which is why retraining posture is a key component to the management of neck pain and headaches in patients with or without a history of whiplash.
Forward head carriage also increases the distance between the back of the head and the headrest in the seated position, especially when the seat is reclined. In a rear-end collision, a gap greater than a half an inch between the head rest and the back of the head increases the probability of injury due to the greater distance the head can hyperextend as it rebounds backwards into the headrest. This makes posture correction of forward head carriage an important aspect of treatment from both a preventative and curative perspective.
So this begs the question, can forward head carriage be corrected? The simple answer is “yes!” One study evaluated the effects of a 16-week resistance and stretching program designed to address forward head posture and protracted shoulder positioning.
Researchers conducted the study in two separate secondary schools with 130 adolescents aged 15–17 years with forward head and protracted shoulder posture. The control group participated in a regular physical education (PE) program while the experimental group attended the same PE classes with the addition of specific exercises for posture correction. The research ream measured the teens’ shoulder head posture from the side using two different validated methods and tracked symptoms using a questionnaire. The results revealed a significant improvement in the shoulder and cervical angle in the experimental group that did not occur in the control group.
The conclusion of the study strongly supports that a 16-week resistance and stretching program is effective in decreasing forward head and protracted shoulder posture in adolescents. This would suggest that a program such as this should be strongly considered in the regular curriculum of PE courses since this is such a common problem.
Doctors of chiropractic are trained to evaluate and manage forward head posture with shoulder protraction. This can prove beneficial in both the prevention as well as management of signs and symptoms associated with a whiplash injury.