
The temporalis muscle is located in the temple area of the skull. It originates on the temporal lines on the parietal bone of the skull, and inserts on the coronoid process of the mandible. It’s main action is to close the jaw. The posterior and middle fibres bilaterally retrude the mandible. Acting individually, this muscle will deviate the mandible to the same side. Trigger points in this muscle refer into the teeth causing hypersensitivity, and into and above the eye and temple, causing headaches.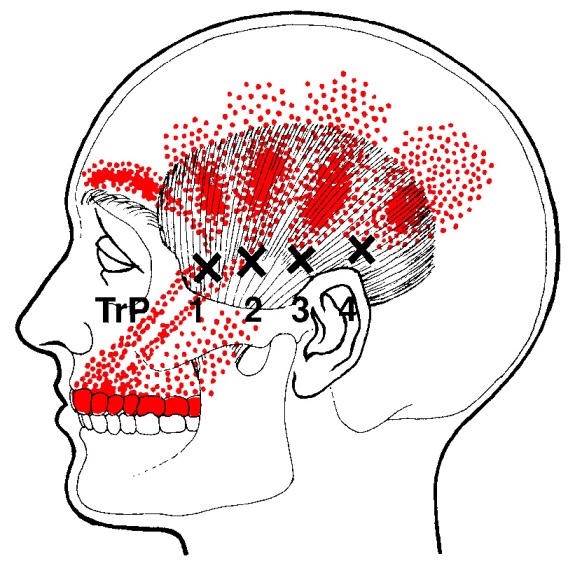
Pain
Runner’s Knee Sucks.
Patellofemoral pain syndrome (PFPS) describes a painful irritation of the cartilage behind your kneecap. Although anyone may be affected, it is often the result of overuse of the knee in sports that require jumping or running so it is sometimes referred to as “Runner’s knee”. PFPS is the most common cause of knee pain in the general population, affecting an estimated 25% of adults.

One of the most common causes of PFPS is an imbalance between the muscles that help to guide your kneecap in its V-shaped groove at the end of your thigh bone. Repeatedly flexing and extending a misaligned kneecap leads to pain, swelling and eventually arthritis. Misalignment of the kneecap (patella) is often secondary to problems in the hip and foot, especially weakness of your gluteal muscles or flat feet.
PFPS produces a dull pain behind the kneecap that is aggravated by prolonged walking, running, squatting, jumping, stair climbing or arising from a seated position. The pain is often worse when walking downhill or down stairs. Longstanding misalignment can cause damage to the cartilage, which results in popping, grinding or giving way.
Conservative care, like the type provided in this office, is generally successful at relieving your symptoms. Initially, it is important for you to minimize activities that provoke your pain, especially running, jumping and activities that stress you into a “knock-kneed” position. Don’t allow your knees to cross in front of your toes when squatting. Some athletes may need to modify their activity to include swimming or bicycling instead of running.
Performing your home exercises consistently is one of the most important things that you can do to help realign the patella, relieve pain and prevent recurrence. The use of home ice or ice massage applied around your kneecap for 10-15 minutes, several times per day may be helpful.
What is Tarsal Tunnel Syndrome?
The tarsal tunnel is the space behind the bump on the inside of your ankle. The tibial nerve lives in this tunnel along with some tendons. Tarsal tunnel syndrome means that the tibial nerve is being irritated within the tunnel. This results in pain, numbness or tingling into your heel and the arch of your foot.
The tibial nerve may be irritated by compression (from trauma , arthritic spurs, or swelling of other tissues within the tunnel), or more commonly by constant stretch (from flat feet). Research has shown that tarsal tunnel pressure increases almost 30 fold in people with flat feet.
 Tarsal tunnel is slightly more common in women, and high heels are suspect. The condition often affects both feet. Conditions like diabetes and thyroid disorders may aggravate nerve problems like tarsal tunnel. Plantar fasciitis commonly accompanies tarsal tunnel syndrome.
The discomfort is often described as “burning”. Symptoms may increase with long periods of standing, running or exercise. Almost half of patients report increased symptoms at night.
Your doctor will make the diagnosis of tarsal tunnel syndrome based on your history and an exam. Your doctor may take an x-ray to rule out other problems like arthritic spurs or a stress fracture. In severe cases, more sophisticated nerve testing may be necessary.
The first goal of treatment is to allow you to return to pain-free activity as soon as possible. The second goal is to correct the mechanical problem that allowed this condition to begin with.
What is knee tendonitis?
Tendons are strong bands of fibrous tissue that connect your muscles to your bones. Your “patellar tendon” connects your kneecap (patella) to your shin bone (tibia). “Patellar tendonopathy” results from repetitive straining and micro-tearing of this connection, resulting in pain and inflammation. The condition is referred to as “jumper’s knee,” since damage is thought to often result from repetitive jumping.


The condition should probably be called “landing knee,” since forces on the patellar tendon are twice as great during landing as compared to those created during take off.
Patellar tendinopathy is common, affecting almost 20% of all athletes with a rate as high as 50% in sports that require repetitive forceful jumping, like basketball and volleyball. The condition may affect one or both knees and may be slightly more common in males.
Weakness in the quadriceps muscle of your thigh can allow excessive bending of your knee when you land following a jump. This places your patellar tendon at a greater risk for injury. Having strong quadriceps muscles protects your knee from excessive flexion and injury.
Symptoms of patellar tendinopathy include pain or swelling just below your kneecap. This may begin without an identifiable injury and may come and go for months or years. Symptoms are usually aggravated by activity, but most athletes have been able to continue playing through the pain. Pain often increases during activities that require strong quadriceps contraction, like jumping, squatting, arising from a seated position, stair climbing, or running. Walking down stairs or running down hill seems to be more bothersome than going up.
Some athletes may have unconsciously learned to protect their knee by developing unnatural jumping mechanics. This could include landing with a more rigid knee, or allowing too much hip flexion. You may need to become more conscious of landing with the right amount of knee flexion with your foot in a neutral position and avoiding excessive hip flexion. Your doctor would be able to answer any questions you have about good jumping mechanics.
Patellar tendon straps, like a Cho-pat, can help reduce stress on your patellar tendon and relieve pain. Three fourths of the people who use patellar tendon straps for patellar tendinitis report improvement.
Patellar tendinopathy is treatable. Patients who follow a well-planned strengthening program show similar outcomes to those who have undergone surgery for the problem. Initially, you may need to decrease your training intensity to help protect your knee. You should stay away from activities that produce more than mild pain. You should avoid complete rest, as this could actually increase your risk of recurrence. Using ice packs or ice massage for 10-15 minutes at a time, especially following activity, may help to reduce inflammation.
What is Sever’s Disease?
Severs disease, also called calcaneal apophysitis, is a painful swelling near the insertion of the Achilles tendon on your heel.
As our bones develop, we have “growth plates” which are softer areas where the bone is still growing. In children, this growth plate is weaker than in adults. This means that children are more likely to suffer growth plate injuries than adults, especially during periods of rapid growth.

The powerful calf muscles attach onto your heel through the Achilles tendon. When your calf muscle contracts (like during running or jumping), it places a shear force on the growth plate of your heel. Severs disease is an irritation to this sensitive growth plate.
Athletically active children, who run and jump frequently in sports like soccer, basketball, gymnastics and track & field are most likely to suffer from this condition. Severs disease is slightly more common in boys and the condition affects both heels about half of the time.
Symptoms usually start as heel pain that gradually worsens during activity. Sometimes this can cause a “limp”. Rest usually temporarily relieves the pain.
Your doctor will make the diagnosis of Severs disease based on your history and an exam. Your doctor may take an x-ray to rule out other injuries like a stress fracture.
The first goal of treatment is to allow you to return to pain-free activity as soon as possible. This may require avoiding stressful activity like running and jumping for a short period of time. Cross training on a bike is usually acceptable. Ice should be applied for 15 minutes after any activity. You should always wear shoes with good arch supports and avoid walking barefoot. Your doctor may recommend a small heel lift to decrease strain on your achilles tendon.
Trigger points in the lateral pterygoid
The lateral pterygoid muscle plays an important role in prober jaw function. It originates on the greater wing of the sphenoid bone and the lateral pterygoid plate, and inserts on the condyloid process of the mandible. It’s action is to pull the head of the mandibular condyle out of the mandibular fossa while opening the jaw. When trigger points develop they refer pain into the temporal mandibular joint and maxillary sinus. This referral is commonly mistaken for TM arthritis. In addition to the referral pain, trigger points in this muscle can also effect proper movement of the jaw.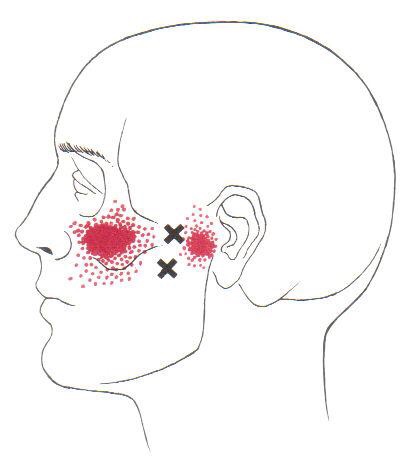

FAI starts you on the road to failure.
Your hip socket or “acetabulum” is covered by smooth, glassy cartilage extending all the way to its outer rim. The term “Femoroacetabular impingement” (FAI) means that this rim of cartilage is being pinched when you move your hip into certain positions. Repetitive pinching results in irritation, tearing, or even detachment of this cartilage from your hip socket.

FAI occurs because of a mismatch between the head of your femur and the socket of your hip. The mismatch may be from an abnormally shaped hip bone (cam deformity), or having too much cartilage on the rim of your hip socket (pincer deformity). Most frequently, FAI results from a combination of both (combined or mixed deformity).
FAI is most common in young active people. Although the deformity may be present on both sides, symptoms are usually one-sided. The condition is equally common among men and women. Symptoms of FAI include a constant dull pain with periods of sharp pain, made worse by activity. Walking, pivoting, prolonged sitting, stair climbing, and impact activities like running or jumping can aggravate your symptoms. Snapping, locking, and clicking are common.
Our office will help direct a rehab program to maximize your chance of recovery. You should attempt to stay active, but avoid activities that aggravate symptoms. You may consider temporarily switching to low-impact activities, like stationary biking or water-walking. You should avoid motions that combine flexion and internal rotation, like- getting out of a car with one leg at a time, swimming the breaststroke, or performing squats. Patients with FAI should avoid excessive stretching, as this could aggravate the condition, but will likely benefit from strengthening exercises in the type of treatment provided in this office.
Spring Cleaning Tips
If you plan on doing a bit of spring cleaning soon, here is our friendly safety reminder: Don’t forget that some chores are a workout, so stretch accordingly before and after. Also, be mindful of your posture throughout your cleaning.
Keep a neutral spine, bend at your knees when lifting heavy items, and never twist your back at unhealthy angles.
I’ve got Shin Splints; what do I do?
Shin splints, also called “Medial Tibial Stress Syndrome,” (MTSS) is caused when the muscles of your lower leg pull too hard on your bone, causing local pain and inflammation. Over half of all leg pain in athletes is caused from shin splints. Up to 1/3 of runners and soldiers experience shin splints at some point in their lifetime.
MTSS is an overuse injury frequently seen in sports involving running, jumping, or frequent stopping & starting, i.e. field hockey, soccer and cross-country. Shin splints do not occur overnight but over a period of time, often show up during the first two or three weeks of training for a new season. Shin splints can occur when there are changes to your exercise regimen, such as an increase in activity, change in shoes or a change in the surface you play on. Some doctors refer to these training areas as “the terrible toos,” – too much, too hard, too long, too fast.

Symptoms of shin splints include tenderness or pain over the inside lower portion of your shin. The discomfort begins at the start of exercise and eases as you continue. Some patients report “bumps” when touching the inner portion of their leg bone. Be sure to tell your doctor if you experience weakness, numbness or cold feet during exercise or find a very small area of sensitivity.
Unfortunately, MTSS usually develops during a time when you are training heavily for a sport or an upcoming event. Continuing this activity will often lead to ongoing problems and decreased performance. Shin splints are now believed to be a forerunner to stress fracture, so adequate rest is critical. You may need to consider non-weight bearing cross training, such as using a stationary cycle or pool running.
When directed, your return to activity should start slowly, beginning with a 1/4 mile run and progressing by 1/4 mile each time you have no pain for two consecutive workouts. You should initially avoid running on hard or uneven surfaces and begin at a lower intensity and distance, increasing by no more than 10-15% per week- first increase distance, then pace, and avoid hard or unlevel surfaces, including hills.
Sports creams and home ice massage may provide some relief. Use ice after any activity. Patients who have flat feet are predisposed to developing shin splints and may need arch supports or orthotics. Avoid using heel cushions in your shoes, as they may increase the recurrence of this problem.
Trigger points in the serratus anterior
The serratus anterior muscle is located along the sides of the ribs. It originates on the outer surface of the upper 8-9ribs, and inserts on the medial border of the scapula. This muscle acts on the scapula in several different ways. First it rotates the scapula to turn the glenoid fossa upward. It also protracted and elevates the scapula. And lastly it helps to prevent wining. This muscle is often shortened from prolonged sitting and work on a computer. Active trigger points in this muscle refer pain locally around the trigger point with spillover down the inside of the arm. Pain can also radiate into the inferior angle of the scapula. 

