What Exercises Should I Do For Fibro?

outdoor-685417_960_720

Fibromyalgia (FM) is a very common, chronic condition where the patient describes “widespread pain” not limited to one area of the body. Hence, when addressing exercises for FM, one must consider the whole body. Perhaps one of the most important to consider is the squat.

If you think about it, we must squat every time we sit down, stand up, get in/out of our car, and in/out of bed. Even climbing and descending steps results in a squat-lunge type of movement.

The problem with squatting is that we frequently lose (or misuse) the proper way to do this when we’re in pain as the pain forces us to compensate, which can cause us to develop faulty movement patterns that can irritate our ankles, knees, hips, and spine (particularly the low back). In fact, performing a squatting exercise properly will strengthen the hips, which will help protect the spine, and also strengthens the glutel muscles, which can help you perform all the daily activities mentioned above.

The “BEST” type of squat is the free-standing squat. This is done by bending the ankles, knees, and hips while keeping a curve in the low back. The latter is accomplished by “…sticking the butt out” during the squat.

Do NOT allow the knees to drift beyond your toes! If you notice sounds coming from your knees they can be ignored IF they are not accompanied by pain. If you do have pain, try moving the foot of the painful knee about six inches (~15 cm) ahead of the other and don’t squat as far down. Move within “reasonable boundaries of pain” by staying away from positions that reproduce sharp, lancinating pain that lingers upon completion.

There are MANY exercises that help FM, but this one is particularly important!

Do I have a tension headache? Or Migranes?

Cervicogenic

Most likely, everyone reading this article has had a headache at one time or another. The American Headache Society reports that nearly 40% of the population suffers from episodic headaches each year while 3% have chronic tension-type headaches. The United States Department of Health and Human Services estimates that 29.5 million Americans experience migraines, but tension headaches are more common than migraines at a frequency of 5 to 1. Knowing the difference between the two is important, as the proper diagnosis can guide treatment in the right direction.

TENSION HEADACHES: These typically result in a steady ache and tightness located in the neck, particularly at the base of the skull, which can irritate the upper cervical nerve roots resulting in radiating pain and/or numbness into the head. At times, the pain can reach the eyes but often stops at the top of the head. Common triggers include stress, muscle strain, or anxiety.

MIGRAINE HEADACHES: Migraines are often much more intense, severe, and sometimes incapacitating. They usually remain on one side of the head and are associated with nausea and/or vomiting. An “aura”, or a pre-headache warning, often comes with symptoms such as a bright flashing light, ringing or noise in the ears, a visual floater, and more. For migraine headaches, there is often a strong family history, which indicates genetics may play a role in their origin.

There are many causes for headaches. Commonly, they include lack of sleep and/or stress and they can also result from a recent injury—such as a car accident, and/or a sports injury—especially when accompanied by a concussion.

Certain things can “trigger” a migraine including caffeine, chocolate, citrus fruits, cured meats, dehydration, depression, diet (skipping meals), dried fish, dried fruit, exercise (excessive), eyestrain, fatigue (extreme), food additives (nitrites, nitrates, MSG), lights (bright, flickering, glare), menstruation, some medications, noise, nuts, odors, onions, altered sleep, stress, watching TV, red wine/alcohol, weather, etc.

Posture is also a very important consideration. A forward head carriage is not only related to headaches, but also neck and back pain. We’ve previously pointed out that every inch (2.54 cm) the average 12 pound head (5.44 kg) shifts forwards adds an EXTRA ten pounds (4.5 kg) of load on the neck and upper back muscles to keep the head upright.

So, what can be done for people who suffer from headaches? First, research shows chiropractic care is highly effective for patients with both types of headaches. Spinal manipulation, deep tissue release techniques, and nutritional counseling are common approaches utilized by chiropractors. Patients are also advised to use some of these self-management strategies at home as part of their treatment plan: the use of ice, self-trigger point therapy, exercise (especially strengthening the deep neck flexors), and nutritional supplements.

Carpal Tunnel Syndrome #3

This week, we will conclude our three-part series on important facts regarding carpal tunnel syndrome (CTS).

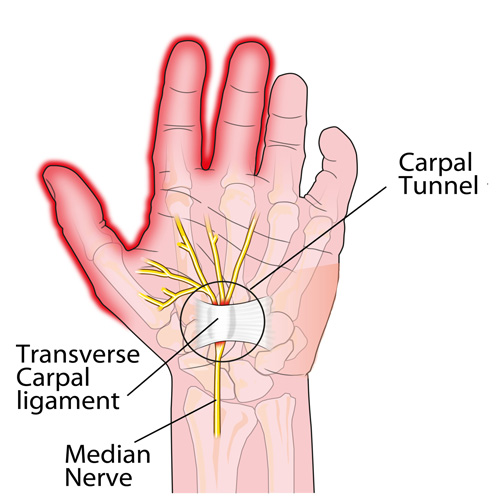
CTS TREATMENT OPTIONS (continued): Aside from the carpal tunnel, there are several places where the median nerve can become compressed as it travels from the neck, down through the shoulder, through tight muscular areas of the upper arm and forearm, and finally through the carpal tunnel at the wrist. In order to achieve good, long-lasting results, treatment must focus on relieving compression at any point along the course of the nerve. This is why chiropractic works SO WELL as it addresses ALL of these areas using manual adjustments, muscle release techniques, and even physical therapy modalities.

CTS PREVENTION: Because there are multiple causes of CTS, prevention must be tailored to each person. For example, if the patient has diabetes mellitus, maintaining a proper blood sugar level is very important because the blood becomes thicker as the sugar levels increase and it simply cannot pass through our small blood vessels (capillaries), especially those located in the feet and hands. This can eventually lead to the need for amputation due to poor circulation and contribute to the numbness associated with diabetic neuropathy.

Similarly, low thyroid function results in a type of swelling called myxedema that can cause or worsen CTS, and keeping the thyroid hormone balanced in the bloodstream is very important. Managing other conditions that create inflammation or swelling, such as rheumatoid and other types of arthritis, will also help prevent CTS from developing or worsening.

Carpal tunnel syndrome can also occur during pregnancy due to the hormonal shifts similar for those taking birth control pills. The PRICE treatment options presented last month can be very helpful for the pregnant mother and represent important non-medication self-care approaches.

Certain occupations that require fast, repetitive work and/or firm gripping can result in carpal tunnel syndrome because of the friction that results in swelling that occurs when the muscle tendons inside the carpal tunnel rub excessively fast together (kind of like starting a fire with two sticks). Modifying the work task until the swelling is controlled is VERY important, as discussed last month.

Other preventative measures include exercises that keep the muscles and tendons in the forearm and inside the carpal tunnel stretched so that the tendons easily slide inside their respective muscle tendon sheaths. This is accomplished by placing the palm side of the hand (elbow straight) on a wall with the fingers pointing downwards while reaching across with the opposite hand and pulling the thumb back until you feel a good firm stretch. Hold this position for 5-10 seconds or until the forearm muscles feel like they are relaxing. Repeat this multiple times a day.

We realize you have a choice in whom you consider for your health care provision and we sincerely appreciate your trust in choosing our service for those needs.  If you, a friend, or family member requires care for Carpal Tunnel Syndrome, we would be honored to render our services.

Carpal Tunnel

What to do about FM #pain?

Fibromyalgia (FM) is a very common condition affecting approximately ten million Americans (2-4% of the population)—with a ratio of about four women to each man with the disease. Part of the diagnosis and treatment challenge is that many of the complaints associated with FM occur in ALL of us at some point, such as fatigue, generalized whole body aches/pains, non-restorative sleep, depression, anxiety, etc. So what is the difference between the FM sufferer and those without it? Let’s take a look!

The primary distinction between patients with FM and the “rest of us” has to do with the word “chronic.” This term means “…persisting for a long time or constantly recurring; long-standing, long-term.” In fact, the term “fibromyalgia” is described as a complex chronic pain disorder that causes widespread pain and tenderness that may present body wide or migrate around the body. It is also known to “wax and wane over time,” meaning it flares up and down, off and on.

The diagnosis of FM is typically made by eliminating every other possible cause. Hence, after blood tests and x-ray or other imaging, the ABSENCE of other problems helps nail down the diagnosis of “primary fibromyalgia.” Then there is “secondary fibromyalgia,” which is DUE TO a known disorder or condition such as after trauma (like a car accident), rheumatoid arthritis, migraine headache, irritable bowel syndrome, “GERD” (which is heart burn due to reflux), pelvic pain, overactive bladder, tempromandibular joint dysfunction (jaw pain, with or without ringing in the ears), or stress. It’s also often accompanied by anxiety, depression, and/or some other mental health condition.

It should be clearly understood that there is no “cure” for FM. It has also been widely reported in many studies that the BEST management approach for FM is through a TEAM of healthcare providers. This team is frequently made up of primary care doctors, doctors of chiropractic, massage therapists, mental / behavioral specialists, physical therapists, and perhaps others (acupuncturist, nutritionist, stress management specialists, and more).

The “general” treatment approach is typically done with medications, cognitive behavioral therapies (CBT), gentle exercise, and manual therapies. Additionally, patients are encouraged to participate in the healing process via self-management strategies that focus on reducing stress and fatigue, optimizing diet, and developing a consistent sleep habit.

Think of the role of the chiropractor as a strong member of the team. A doctor of chiropractic can offer many of the known methods of managing FM described above, as their training includes diet and nutrition, stress management, exercise training, and ability to provide “whole person care.” Treatments delivered in the chiropractic setting like spinal manipulation, mobilization, and massage offer GREAT relief to FM patients! Again, coordinating care between various providers is the best approach, but you need someone willing and able to do that. A doctor of chiropractic is a great choice!

It is very difficult to manage FM on your own. Let a doctor of chiropractic tailor a treatment plan that is appealing to you and your specific interests. Managing FM is definitely NOT a “…one size fits all” approach like an inhaler is for asthma. Each individual’s situation is too highly unique!60+ Yoga

Can Chiro Help My Headache?

Migrane

Everyone, well at least almost everyone, has had headaches from time to time, and we all know how miserable they can make us feel. In fact, at some point in time, 9 out of 10 Americans suffer from headaches that range between mild and dull to throbbing, intense, and debilitating, sometimes to the point of requiring bed rest in a dark, quiet room.

The common reflex is to reach for that bottle of pills and pray the headache subsides so you don’t have to call in sick and lose another day of productivity when you have so much to do. Unfortunately, between the side effects of many medications designed to help headaches and the pain associated with the headache, this approach is frequently NOT the answer. So what is?

The good news is that many studies have identified spinal manipulation therapy (SMT), the main type of care utilized by chiropractors, as being very effective for popular types of headaches—in particular tension-type headaches that arise in the neck. An important 2001 study reported that SMT provided almost immediate relief for headaches that arose in the neck with SIGNIFICANTLY fewer side effects and longer-lasting results compared with commonly prescribed medications.

Another interesting study that found similar results included tracking the prevalence/frequency of headaches after treatment stopped. The authors of the study reported the patients receiving SMT had continued to experience sustained benefits throughout the following weeks, and even months, in contrast to those in a medication treatment group where headaches came back almost immediately after they discontinued treatment.

The most commonly prescribed medication for tension-type headaches are non-steroidal anti-inflammatory drugs (NSAIDs). Common over-the-counter options include ibuprofen (Advil, Nuprin, etc.) and Aleve (Naproxen). For those who can’t take NSAIDs because of blood thinning and/or stomach-liver-kidney problems, doctors commonly prescribe acetaminophen (Tylenol), but it can be hard on the liver and kidneys, especially when taken over time.

So, what can you expect from a visit to a chiropractor for your headaches? The typical approach begins with a thorough history and examination with an emphasis of evaluating the neck and its associated function. Your doctor of chiropractic may also perform tests designed to reduce pain and some that provoke a pain response to identify the “pain generator” or cause!

Because each patient is unique, the type of care provided will be individually determined based on the findings, the patient’s age, comfort, and preference of both the provider and patient.

So, the next time you find yourself reaching for pills because of headaches, remember that there are better options! Give chiropractic a try. You’ll be GLAD you did!!!

We realize you have a choice in whom you consider for your health care provision and we sincerely appreciate your trust in choosing our service for those needs.  If you, a friend, or family member requires care for neck pain or headaches, we would be honored to render our services.

Carpal Tunnel Syndrome #2

Healthcare providers tend to agree that in non-emergency situations, patients with conditions like Carpal Tunnel Syndrome (CTS) should try non-surgical treatments before consulting with a surgeon. The “PRICE” concept, that is Protect, Rest, Ice, Compress, & Elevate can be applied to most injuries, including CTS, especially in the acute/inflammatory stage. However, many of these principles also apply in the chronic stage (more than three months) of CTS.

PROTECT: For the CTS patient, many doctors commonly prescribe a wrist cock-up splint to be worn overnight, which may surprise some of you! During the day, depending on the type of work you do, a wrist splint can actually get in the way and result in increased symptoms, and at times, cause bruising at both ends of the splint (mid-forearm & mid-hand). The primary reason to use the splint at night is that one cannot control the position of their wrist during sleep, and it can often wind up bent. This increases the pressure inside the carpal tunnel up to six to eight times more than normal, potentially causing enough pain and tingling to disturb sleep. The splint guarantees a neutral wrist position, which significantly improves sleep quality and allows healing to occur.

REST: The use of a splint allows the swollen median nerve to heal. However, in order to allow the wrist to rest so inflammation can subside and the condition can fully heal, patients often need to modify their daily activities, at least for a short time. This may require job restrictions, especially if the occupation involves a fast repetitive motion type of tasks and/or forceful gripping.

ICE: The use of an “ice cup”—or an ice cube held with a washcloth to protect the fingertips from getting cold—is by far the most effective approach. Rub the ice directly on the skin over the carpal tunnel so that you experience the four stages of cooling: Cold, Burning, Aching, and Numb (C-BAN). This usually takes about four minutes, and it’s important to stop when numbness occurs, as the next stage of cooling is frostbite. This can be repeated multiple times a day and is often as effective as cortisone shots with fewer side effects (and less pain!).

COMPRESS: The wrist cock-up splint can offer some compression, but an elastic carpal tunnel wrist band will not usually interfere with most activities of daily living. Some versions include a thumb loop to keep the wrist band in place, but that may get in the way. A version without the thumb loop also works very well.

EXERCISE: Exercises performed at home and work can significantly help manage the condition. (Note: For injuries like a sprained ankle, E typically stands for ELEVATE, though it’s not practical for the CTS patient.)

Tune in next month for the unique techniques that chiropractic offers to the non-surgical care of CTS as well as the importance of preventative measures and research.

We realize you have a choice in whom you consider for your health care provision and we sincerely appreciate your trust in choosing our service for those needs.  If you, a friend, or family member requires care for Carpal Tunnel Syndrome, we would be honored to render our services.


480px-Carpal_Tunnel_Syndrome

What is Cervical Spondylosis?

CSpine

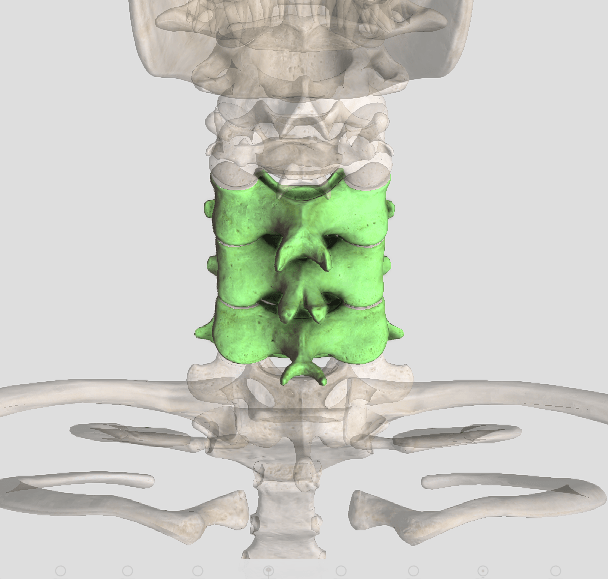
Cervical spondylosis (CS) is another term for osteoarthritis (OA) of the neck. It is a common, age-related condition that you will probably develop if you live long enough. Or, if you suffered a neck injury as a youth, it can develop within five to ten years of the injury, depending on the severity. According to the Mayo Clinic, CS or OA affects more than 85% of people over 60 years old, and that is probably a conservative estimate!

Common symptoms associated with CS/OA vary widely from no symptoms whatsoever to debilitating pain and stiffness. For example, when CS crowds the holes through which the nerves and/or spinal cord travel, it creates a condition called spinal stenosis that can result in numbness, tingling, and/or weakness. In severe cases, this can even affect bowel or bladder control (which is an EMERGENCY)!

CS occurs when the normal slippery, shiny cartilage surfaces of the joint(s) gradually thin and eventually wear away. Bone spurs often form, which results from the body trying to stabilize an unstable joint. In some cases, the spurs can actually fuse a joint, which often helps reduce pain. (Bone spurs can also form if the intervertebral disks or shock-absorbing pads between the vertebrae are injured or become dehydrated due to arthritic conditions.)

Risk factors associated with CS include: aging, injury, years of heavy lift/carry job demands, and jobs and/or hobbies that require the neck to be outside of a neutral position (like years of pinching a phone between the ear and shoulder). Genetics and bad habits (like smoking) also play a role in CS. Obesity and inactivity also worsens the severity of CS symptoms.

The good news is that even though most of us will have CS, it is usually NOT a disabling condition. However, CS may interfere with our normal activities. Depending on its location, pain may feel worse in certain positions, like when sneezing or coughing or with movements like rotation or looking upwards.

Stiffness is a common symptom, which can vary with weather changes. Too little as well as too much activity can be a problem, but the BEST way to self-manage CS is to keep active! Range of motion exercises, strength training, and walking all help reduce the symptoms of CS.

Doctors of chiropractic are trained to identify CS/OA. Gentle manipulation, mobilization, nutritional counseling, exercise training, modalities (and more) can REALLY HELP!

I have Low Back Pain. Why?

265

Low back pain (LBP) can arise from disks, nerves, joints, and the surrounding soft tissues. To simplify the task of determining “What is causing my LBP?” the Quebec Task Force recommends that LBP be divided into three main categories: 1) Mechanical LBP; 2) Nerve root related back pain; and 3) Pathology or fracture. We will address the first two, as they are most commonly managed by chiropractors.
Making the proper diagnosis points your doctor in the right direction regarding treatment. It avoids time wasted by treating an unrelated condition, which runs the risk of increased chances of a poor and/or prolonged recovery. Low back pain is no exception! The “correct” diagnosis allows treatment to be focused and specific so that it will yield the best results.
Mechanical low back pain is the most commonly seen type of back pain, and it encompasses pain that arises from sprains, strains, facet and sacroiliac (SI) syndromes, and more. The main difference between this and nerve root-related LBP is the ABSENCE of a pinched nerve. Hence, pain typically does NOT radiate, and if it does, it rarely goes beyond the knee and normally does not cause weakness in the leg.
The mechanism of injury for both types of LBP can occur when a person does too much, maintains an awkward position for too long, or over bends, lifts, and/or twists. However, LBP can also occur “insidiously” or for seemingly no reason at all. However, in most cases, if one thinks hard enough, they can identify an event or a series of “micro-traumas” extending back in time that may be the “cause” of their current low back pain issues.
Nerve root-related LBP is less common but it is often more severe—as the pain associated with a pinched nerve is often very sharp, can radiate down a leg often to the foot, and cause numbness, tingling, and muscle weakness. The location of the weakness depends on which nerve is pinched. Think of the nerve as a wire to a light and the switch of the nerve is located in the back where it exits the spine. When the switch is turned on (the nerve is pinched), and the “light” turns on—possibly in the outer foot, middle foot, inner foot, or front, back or side of the thigh. In fact, there are seven nerves that innervate or “run” into our leg, so usually, a very specific location “lights up” in the limb.
Determining the cause of your low back pain helps your doctor of chiropractic determine which treatments may work best to alleviate your pain as well as where such treatments can be focused.

Meds or Chiro first?

Head and Neck

Although both medication and chiropractic are utilized by neck pain sufferers, not everyone wants to or can take certain medications due to unwanted side effects. For those who aren’t sure what to do, wouldn’t it be nice if research was available that could answer the question posted above? Let’s take a look!

When people have neck pain, they have options as to where they can go for care. Many seek treatment from their primary care physician (PCP). The PCP’s approach to neck pain management usually results in a prescription that may include an anti-inflammatory drug (like ibuprofen or Naproxen), a muscle relaxant (like Flexeril / cyclobenzaprine), and/or a pain pill (like hydrocodone / Vicodin). The choice of which medication a PCP recommends hinges on the patient’s presentation, patient preference (driven from advertisements or prior experiences), and/or the PCP’s own preference.

Although it’s becoming increasingly common to have a PCP refer a neck pain patient for chiropractic care, this still does not happen for all neck pain patients in spite of strong research supporting the significant benefits of spinal manipulation to treat neck pain. One such study compared spinal manipulation, acupuncture, and anti-inflammatory medication with the objective of assessing the long-term benefits (at one year) of these three approaches in patients with chronic (>13 weeks) neck pain. The study randomly divided 115 patients into one of three groups that were all treated for nine weeks. Comparison at the one-year point showed that ONLY those who received spinal manipulation had maintained long-term benefits based on a review of seven main outcome measures. The study concludes that for patients with chronic neck pain, spinal manipulation was the ONLY treatment that maintained a significant long-term (one-year) benefit after nine weeks of treatment!

In a 2012 study published in medical journal The Annals of Internal Medicine, 272 acute or sub-acute neck pain patients received one of three treatment approaches: medication, exercise with advice from a health care practitioner, or chiropractic care. Participants were treated for twelve weeks, with outcomes assessed at 2, 4, 8, 12, 26, and 52 weeks. The patients in the chiropractic care and exercise groups significantly outperformed the medication group at the 26-week point AND had more than DOUBLE the likelihood of complete neck pain relief. However, at the one-year point, ONLY the chiropractic group continued to demonstrate long-term benefits! The significant benefits achieved from both exercise and chiropractic treatments when compared with medication make sense as both address the cause of neck pain as opposed to only masking the symptoms.

With results of these studies showing acute, subacute, as well as chronic neck pain responding BEST to chiropractic care, it only makes sense to TRY THIS FIRST!

Whole Body Approach to Fibromyalgia

Fibromyalgia is a complicated disorder that’s difficult to diagnose because it involves multiple body systems. As a result, there are a myriad of factors in the body that can play a role in a patient’s symptoms. That said, it’s best to take a whole body approach when it comes to treating a complex condition like FM, starting with the nervous system.

When a patient presents to a chiropractor, the initial examination will look at the body as a whole and will not be limited the main area of complaint. This includes a postural examination in regards to individual leg length (to see if one is shorter); the height of the pelvis, shoulder, and occiput (head); and a gait assessment to evaluate the function of the foot, ankle, knee, hip/pelvis, spine, and head.

Because the nervous system is housed in the spine and cranium, chiropractors specifically look at how the spine compensates for abnormal function elsewhere in the body. When spinal segmental dysfunction is present, altered neurological function often coincides, which results in the symptoms that drive people to the office.

The benefits of spinal manipulative therapy (SMT)—the primary form of treatment delivered by doctors of chiropractic—have been recognized by all other healthcare professions including medical doctors, physical therapists, and osteopathic physicians. In fact, referring patients to chiropractors for SMT has become very commonplace in the healthcare environment. Research has proven SMT to be a FIRST course of care and highly recommended for MANY complaints, especially low back, mid-back, and neck pain, headaches, and many more!

Because fibromyalgia (FM) involves the WHOLE BODY—hence its definition of “wide spread pain,” chiropractic offers a unique approach because it too benefits the whole body by restoring function to the nervous system. For example, when balance is off due to a short leg (this affects 90% of the population to some degree), it can tilt the pelvis, which then places stress on the spine so that it must curve (scoliosis) to keep the head level. Correcting the short leg with a heel lift can restore balance to the pelvis, take pressure off the spine, and relieve some of a patient’s pain symptoms.

In prior articles, we have looked at the many benefits chiropractic offers the FM patient in addition to SMT and other manual therapies. Some of these include tips for improving sleep, exercise training (very important in managing FM), diet—specifically an anti-inflammatory diet (rich in anti-oxidants)—and supplementation (such as magnesium, malic acid, omega-3 fatty acids, vitamin D3, Co-enzyme Q10, and more).

Most importantly, studies show that the FM patient is BEST served when a “team” of healthcare professionals work together on behalf of the FM patient. Depending on a patient’s needs, the team can include a doctor of chiropractic, a primary care doctor, a massage therapist, a clinical psychologist, and others.