I get dizzy when I have a headache. Should I worry?

​Vertigo_view_03,_Andels_Hotel_Łódź.jpg

Dizziness, neck pain, and headaches are very common symptoms that may or may not occur at the same time. Though this interrelationship exists, this month’s article will focus primarily on dizziness, particularly related to dizziness that occurs after standing.

First, it is important to point out that it is VERY common to be light headed or dizzy when standing up too fast, which is typically referred to as orthostatic hypotension (OH). OH is frequently referred to as a benign symptom, but new information may challenge this thought.

Let’s review what happens. When we are lying down, our heart does not have to work as hard as when we are upright; therefore, our blood pressure (BP) is usually lower while we lay in bed. When standing up, blood initially pools in the legs until an increase in blood pressure brings oxygen to the brain. This either resolves or prevents dizziness.

Orthostatic hypotension is defined as a blood pressure drop of >20 mm Hg systolic (the upper number—heart at FULL contraction), 10 mm Hg diastolic (lower number—heart at FULL rest), or both. This typically occurs within seconds to a few minutes after rising to a standing position.

There are two types of OH—delayed OH (DOH) where the onset of symptoms are not immediate but occur within three minutes of standing and “full” OH, which is more serious and occurs immediately upon rising. According to a 2016 study published in the prestigious journal Neurology, researchers reviewed the medical records of 165 people who had undergone autonomic nervous system testing for dizziness. The subjects averaged 59 years of age, and 48 were diagnosed with DOH, 42 with full OH, and 75 subjects didn’t have either condition.

During a ten-year follow-up, 54% of the DOH group progressed to OH, of which 31% developed a degenerative brain condition such as Parkinson’s disease or dementia. Those with initial DOH who also had diabetes were more likely to develop full OH vs. those without diabetes.

The early death rate in this 165 patient group was 29% for those with DOH, 64% with full OH, vs. 9% for those with neither diagnosed condition. The authors point out that those initially diagnosed with DOH who did NOT progress into full OH were given treatment that may have improved their blood pressure.

The authors state that a premature death might be avoided by having DOH and OH diagnosed and properly managed as early as possible. They point out that a prospective study is needed since this study only looked back at medical records of subjects who had nervous system testing performed at a specialized center, and therefore, these findings may not apply to the general population.

The value of this study is that this is the FIRST time a study described OH (or DOH) as a potentially serious condition with recommendations NOT to take OH/DOH lightly or view it as a benign condition. Since doctors see this a lot, a closer evaluation of the patient is in order.

Do You Have CTS?

​Carpal tunnel syndrome (CTS) can be an extremely painful and activity-limiting condition. It affects many people of all ages and genders, though women are affected more often than men. But how do you know if what you are suffering from is truly CTS or if it’s another condition that’s producing the symptoms in your hand or wrist?

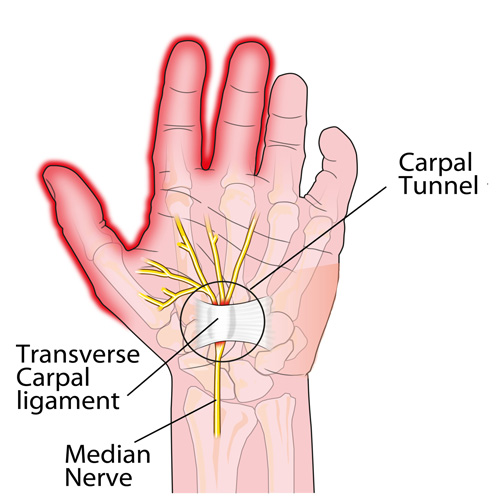
Carpal tunnel syndrome occurs when the median nerve is compressed as it passes through the wrist. However, the median nerve travels out of the neck, through the shoulder, elbow, and forearm before it passes through the wrist and into the hand. Pinching of the median nerve ANYWHERE along its course can give rise to the signs and symptoms of CTS including numbness, tingling, and/or pain into the hand and index, third, and thumb-side half of the fourth digits, and sometimes the thumb. If the pinch is significant enough, weakness can also occur. Sometimes the median nerve can become compressed at both the wrist and other body sites as it travels from the spinal cord to your hand, that’s why it’s important for a doctor to check for impingements along the entire course of the nerve.

But compression of the median nerve isn’t the only thing that can produce symptoms in the hand. Here are a couple of the more common conditions that are often confused with CTS:

1)  Ulnar neuropathy: This is pinching of the ulnar nerve (at the neck, shoulder, elbow, or wrist) but this gives rise to a similar numbness/tingling BUT into the pinky-side of the fourth and the fifth fingers (not the thumb-side of the hand). The most common pinch location is either at the neck or the inner elbow, the latter of which is called “cubital tunnel syndrome” or CuTS.

2)  Tendonitis: There are a total of nine tendons that pass through the carpal tunnel that help us grip or make a fist. Similarly, there are five main tendons on the back side of the hand that allow us to open our hands and spread our fingers. ANY of these tendons can get strained or torn, which results in swelling and pain as well as limited function BUT there is usually NO NUMBNESS/TINGLING!

3)  DeQuervain’s disease: This is really a tendonitis of an extensor tendon of the thumb and its synovial sheath that lubricates it resulting in a “tenosynovitis.” This creates pain with thumb movements, especially if you grasp your thumb in the palm of your hand and then bend your wrist sideways towards the pinky-side of the hand.

Chiropractors are well-trained to diagnose and treat patients with CTS. And if you don’t have CTS but another condition listed above, they can offer treatment (or a referral, if necessary) to help resolve it so you can return to your normal activities as soon as possible.

DOn't know

What Exercises Should I Do For Fibro?

outdoor-685417_960_720

​Fibromyalgia (FM) is a very common, chronic condition where the patient describes “widespread pain” not limited to one area of the body. Hence, when addressing exercises for FM, one must consider the whole body. Perhaps one of the most important to consider is the squat.

If you think about it, we must squat every time we sit down, stand up, get in/out of our car, and in/out of bed. Even climbing and descending steps results in a squat-lunge type of movement.

The problem with squatting is that we frequently lose (or misuse) the proper way to do this when we’re in pain as the pain forces us to compensate, which can cause us to develop faulty movement patterns that can irritate our ankles, knees, hips, and spine (particularly the low back). In fact, performing a squatting exercise properly will strengthen the hips, which will help protect the spine, and also strengthens the glutel muscles, which can help you perform all the daily activities mentioned above.

The “BEST” type of squat is the free-standing squat. This is done by bending the ankles, knees, and hips while keeping a curve in the low back. The latter is accomplished by “…sticking the butt out” during the squat.

Do NOT allow the knees to drift beyond your toes! If you notice sounds coming from your knees they can be ignored IF they are not accompanied by pain. If you do have pain, try moving the foot of the painful knee about six inches (~15 cm) ahead of the other and don’t squat as far down. Move within “reasonable boundaries of pain” by staying away from positions that reproduce sharp, lancinating pain that lingers upon completion.

There are MANY exercises that help FM, but this one is particularly important!

Do I have a tension headache? Or Migranes?

Cervicogenic

​Most likely, everyone reading this article has had a headache at one time or another. The American Headache Society reports that nearly 40% of the population suffers from episodic headaches each year while 3% have chronic tension-type headaches. The United States Department of Health and Human Services estimates that 29.5 million Americans experience migraines, but tension headaches are more common than migraines at a frequency of 5 to 1. Knowing the difference between the two is important, as the proper diagnosis can guide treatment in the right direction.

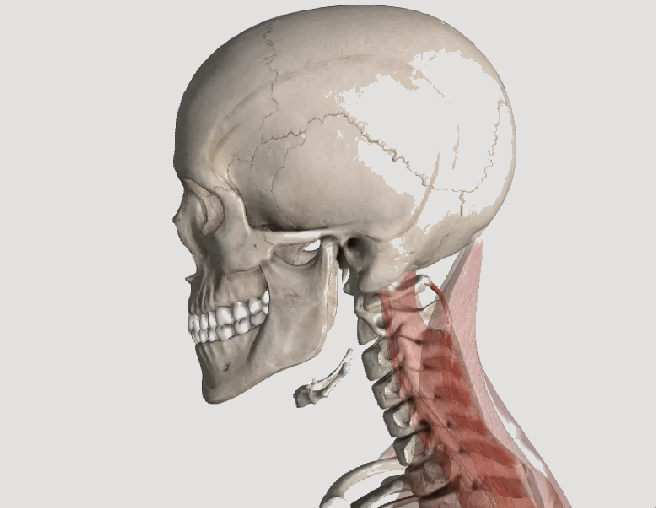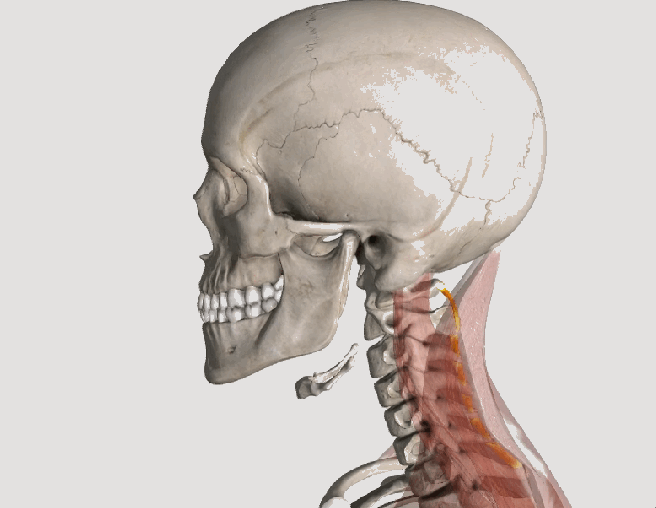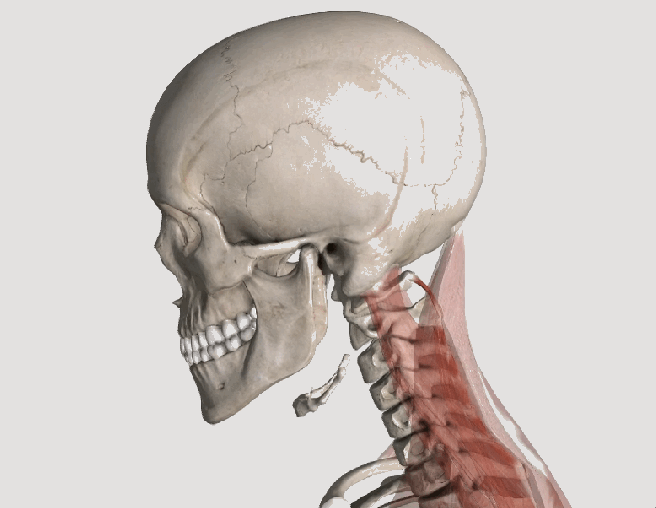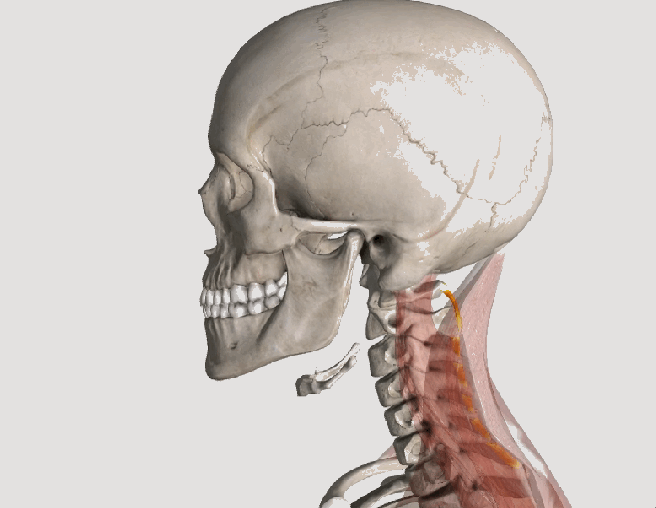
TENSION HEADACHES: These typically result in a steady ache and tightness located in the neck, particularly at the base of the skull, which can irritate the upper cervical nerve roots resulting in radiating pain and/or numbness into the head. At times, the pain can reach the eyes but often stops at the top of the head. Common triggers include stress, muscle strain, or anxiety.

MIGRAINE HEADACHES: Migraines are often much more intense, severe, and sometimes incapacitating. They usually remain on one side of the head and are associated with nausea and/or vomiting. An “aura”, or a pre-headache warning, often comes with symptoms such as a bright flashing light, ringing or noise in the ears, a visual floater, and more. For migraine headaches, there is often a strong family history, which indicates genetics may play a role in their origin.

There are many causes for headaches. Commonly, they include lack of sleep and/or stress and they can also result from a recent injury—such as a car accident, and/or a sports injury—especially when accompanied by a concussion.

Certain things can “trigger” a migraine including caffeine, chocolate, citrus fruits, cured meats, dehydration, depression, diet (skipping meals), dried fish, dried fruit, exercise (excessive), eyestrain, fatigue (extreme), food additives (nitrites, nitrates, MSG), lights (bright, flickering, glare), menstruation, some medications, noise, nuts, odors, onions, altered sleep, stress, watching TV, red wine/alcohol, weather, etc.

Posture is also a very important consideration. A forward head carriage is not only related to headaches, but also neck and back pain. We’ve previously pointed out that every inch (2.54 cm) the average 12 pound head (5.44 kg) shifts forwards adds an EXTRA ten pounds (4.5 kg) of load on the neck and upper back muscles to keep the head upright.

So, what can be done for people who suffer from headaches? First, research shows chiropractic care is highly effective for patients with both types of headaches. Spinal manipulation, deep tissue release techniques, and nutritional counseling are common approaches utilized by chiropractors. Patients are also advised to use some of these self-management strategies at home as part of their treatment plan: the use of ice, self-trigger point therapy, exercise (especially strengthening the deep neck flexors), and nutritional supplements.

Carpal Tunnel Syndrome #3

​This week, we will conclude our three-part series on important facts regarding carpal tunnel syndrome (CTS).

CTS TREATMENT OPTIONS (continued): Aside from the carpal tunnel, there are several places where the median nerve can become compressed as it travels from the neck, down through the shoulder, through tight muscular areas of the upper arm and forearm, and finally through the carpal tunnel at the wrist. In order to achieve good, long-lasting results, treatment must focus on relieving compression at any point along the course of the nerve. This is why chiropractic works SO WELL as it addresses ALL of these areas using manual adjustments, muscle release techniques, and even physical therapy modalities.

CTS PREVENTION: Because there are multiple causes of CTS, prevention must be tailored to each person. For example, if the patient has diabetes mellitus, maintaining a proper blood sugar level is very important because the blood becomes thicker as the sugar levels increase and it simply cannot pass through our small blood vessels (capillaries), especially those located in the feet and hands. This can eventually lead to the need for amputation due to poor circulation and contribute to the numbness associated with diabetic neuropathy.

Similarly, low thyroid function results in a type of swelling called myxedema that can cause or worsen CTS, and keeping the thyroid hormone balanced in the bloodstream is very important. Managing other conditions that create inflammation or swelling, such as rheumatoid and other types of arthritis, will also help prevent CTS from developing or worsening.

Carpal tunnel syndrome can also occur during pregnancy due to the hormonal shifts similar for those taking birth control pills. The PRICE treatment options presented last month can be very helpful for the pregnant mother and represent important non-medication self-care approaches.

Certain occupations that require fast, repetitive work and/or firm gripping can result in carpal tunnel syndrome because of the friction that results in swelling that occurs when the muscle tendons inside the carpal tunnel rub excessively fast together (kind of like starting a fire with two sticks). Modifying the work task until the swelling is controlled is VERY important, as discussed last month.

Other preventative measures include exercises that keep the muscles and tendons in the forearm and inside the carpal tunnel stretched so that the tendons easily slide inside their respective muscle tendon sheaths. This is accomplished by placing the palm side of the hand (elbow straight) on a wall with the fingers pointing downwards while reaching across with the opposite hand and pulling the thumb back until you feel a good firm stretch. Hold this position for 5-10 seconds or until the forearm muscles feel like they are relaxing. Repeat this multiple times a day.

We realize you have a choice in whom you consider for your health care provision and we sincerely appreciate your trust in choosing our service for those needs.  If you, a friend, or family member requires care for Carpal Tunnel Syndrome, we would be honored to render our services.

Carpal Tunnel

Can Adjustments Help Relieve Neck Pain?

​There have been MANY studies conducted on the benefits and efficacy of spinal manipulation to treat back pain—so much so that many medical doctors frequently refer patients with back pain to chiropractors for this service. But what about neck pain?

Although it’s taken a little longer to compile the evidence, there is now substantial research to support that spinal manipulation for neck pain is equally effective as it is for low back pain in regards to improving pain levels, function, and quality of life.

Multiple reviews and meta-analyses (studies that evaluate the research over a series of years) indicate that mobilization, manipulation, and exercise all work alone but appear to give the best long-term benefits when used in combination with each other.

In the acute and subacute stages of neck pain, studies show cervical manipulation is more effective than various combinations of analgesics, muscle relaxants, and nonsteroidal anti-inflammatory drugs (NSAIDs) for improving pain and function in both the short and intermediate term.

Studies show that thoracic or mid-back manipulation is also very helpful for patients with neck pain. Chiropractic approaches often include a combination of spinal manipulation, manual cervical traction, figure-8 mobilization, and deep tissue trigger point/active release forms of therapy.

As noted above, the inclusion of exercise yields the best long-term benefits, especially for chronic neck pain.

One such exercise is Cranio-cervical flexion (deep neck flexor strengthening): Tuck the chin inwards, pushing the mid part of the neck backward with or without resisting into your fingers/hands or a towel wrapped around the neck. A gradual crescendo of pressure followed by a gradual release (or decrescendo) works well!

Another great exercise is Fiber Stretching: Side-bend the head and neck while applying gentle over-pressure while simultaneously reaching downward with the opposite arm/hand, searching for tight muscle fibers. Try combining forward and backward rotations and chin glide head movements while applying the over-pressure/reach combinations, and work each tight fiber until it loosens up.

There are many other exercises your doctor of chiropractic can show you, but these are a great start!

What Causes Low Back Pain?

​236

Low back pain (LBP) can arise from disks, nerves, joints, and the surrounding soft tissues.
To simplify the task of determining “What is causing my LBP?” the Quebec Task Force recommends that LBP be divided into three main categories: 1) Mechanical LBP; 2) Nerve root related back pain; and 3) Pathology or fracture. We will address the first two, as they are most commonly managed by chiropractors.
Making the proper diagnosis points your doctor in the right direction regarding treatment. It avoids time wasted by treating an unrelated condition, which runs the risk of increased chances of a poor and/or prolonged recovery. Low back pain is no exception! The “correct” diagnosis allows treatment to be focused and specific so that it will yield the best results.
Mechanical low back pain is the most commonly seen type of back pain, and it encompasses pain that arises from sprains, strains, facet and sacroiliac (SI) syndromes, and more. The main difference between this and nerve root-related LBP is the ABSENCE of a pinched nerve. Hence, pain typically does NOT radiate, and if it does, it rarely goes beyond the knee and normally does not cause weakness in the leg.
The mechanism of injury for both types of LBP can occur when a person does too much, maintains an awkward position for too long, or over bends, lifts, and/or twists. However, LBP can also occur “insidiously” or for seemingly no reason at all. However, in most cases, if one thinks hard enough, they can identify an event or a series of “micro-traumas” extending back in time that may be the “cause” of their current low back pain issues.
Nerve root-related LBP is less common but it is often more severe—as the pain associated with a pinched nerve is often very sharp, can radiate down a leg often to the foot, and cause numbness, tingling, and muscle weakness. The location of the weakness depends on which nerve is pinched. Think of the nerve as a wire to a light and the switch of the nerve is located in the back where it exits the spine. When the switch is turned on (the nerve is pinched), and the “light” turns on—possibly in the outer foot, middle foot, inner foot, or front, back or side of the thigh. In fact, there are seven nerves that innervate or “run” into our leg, so usually, a very specific location “lights up” in the limb.
Determining the cause of your low back pain helps your doctor of chiropractic determine which treatments may work best to alleviate your pain as well as where such treatments can be focused.

Whiplash and Your Posture

WRD 2.gif​

Posture assessment is a key component of the chiropractic examination, and the posture of the head and neck is especially important for a patient recovering from a whiplash injury. Forward head carriage describes a state in which the head sits more forward on the shoulders than it should. In order for the muscles in the neck and shoulders to keep the head upright, they must work harder. This added strain can increase one’s risk for neck pain and headaches, which is why retraining posture is a key component to the management of neck pain and headaches in patients with or without a history of whiplash.

Forward head carriage also increases the distance between the back of the head and the headrest in the seated position, especially when the seat is reclined. In a rear-end collision, a gap greater than a half an inch between the head rest and the back of the head increases the probability of injury due to the greater distance the head can hyperextend as it rebounds backwards into the headrest.  This makes posture correction of forward head carriage an important aspect of treatment from both a preventative and curative perspective.

So this begs the question, can forward head carriage be corrected?  The simple answer is “yes!” One study evaluated the effects of a 16-week resistance and stretching program designed to address forward head posture and protracted shoulder positioning.

Researchers conducted the study in two separate secondary schools with 130 adolescents aged 15–17 years with forward head and protracted shoulder posture. The control group participated in a regular physical education (PE) program while the experimental group attended the same PE classes with the addition of specific exercises for posture correction. The research ream measured the teens’ shoulder head posture from the side using two different validated methods and tracked symptoms using a questionnaire. The results revealed a significant improvement in the shoulder and cervical angle in the experimental group that did not occur in the control group.

The conclusion of the study strongly supports that a 16-week resistance and stretching program is effective in decreasing forward head and protracted shoulder posture in adolescents.  This would suggest that a program such as this should be strongly considered in the regular curriculum of PE courses since this is such a common problem.

Doctors of chiropractic are trained to evaluate and manage forward head posture with shoulder protraction. This can prove beneficial in both the prevention as well as management of signs and symptoms associated with a whiplash injury.

What to do about FM #pain?

​Fibromyalgia (FM) is a very common condition affecting approximately ten million Americans (2-4% of the population)—with a ratio of about four women to each man with the disease. Part of the diagnosis and treatment challenge is that many of the complaints associated with FM occur in ALL of us at some point, such as fatigue, generalized whole body aches/pains, non-restorative sleep, depression, anxiety, etc. So what is the difference between the FM sufferer and those without it? Let’s take a look!

The primary distinction between patients with FM and the “rest of us” has to do with the word “chronic.” This term means “…persisting for a long time or constantly recurring; long-standing, long-term.” In fact, the term “fibromyalgia” is described as a complex chronic pain disorder that causes widespread pain and tenderness that may present body wide or migrate around the body. It is also known to “wax and wane over time,” meaning it flares up and down, off and on.

The diagnosis of FM is typically made by eliminating every other possible cause. Hence, after blood tests and x-ray or other imaging, the ABSENCE of other problems helps nail down the diagnosis of “primary fibromyalgia.” Then there is “secondary fibromyalgia,” which is DUE TO a known disorder or condition such as after trauma (like a car accident), rheumatoid arthritis, migraine headache, irritable bowel syndrome, “GERD” (which is heart burn due to reflux), pelvic pain, overactive bladder, tempromandibular joint dysfunction (jaw pain, with or without ringing in the ears), or stress. It’s also often accompanied by anxiety, depression, and/or some other mental health condition.

It should be clearly understood that there is no “cure” for FM. It has also been widely reported in many studies that the BEST management approach for FM is through a TEAM of healthcare providers. This team is frequently made up of primary care doctors, doctors of chiropractic, massage therapists, mental / behavioral specialists, physical therapists, and perhaps others (acupuncturist, nutritionist, stress management specialists, and more).

The “general” treatment approach is typically done with medications, cognitive behavioral therapies (CBT), gentle exercise, and manual therapies. Additionally, patients are encouraged to participate in the healing process via self-management strategies that focus on reducing stress and fatigue, optimizing diet, and developing a consistent sleep habit.

Think of the role of the chiropractor as a strong member of the team. A doctor of chiropractic can offer many of the known methods of managing FM described above, as their training includes diet and nutrition, stress management, exercise training, and ability to provide “whole person care.” Treatments delivered in the chiropractic setting like spinal manipulation, mobilization, and massage offer GREAT relief to FM patients! Again, coordinating care between various providers is the best approach, but you need someone willing and able to do that. A doctor of chiropractic is a great choice!

It is very difficult to manage FM on your own. Let a doctor of chiropractic tailor a treatment plan that is appealing to you and your specific interests. Managing FM is definitely NOT a “…one size fits all” approach like an inhaler is for asthma. Each individual’s situation is too highly unique!60+ Yoga

Can Chiro Help My Headache?

​Migrane

Everyone, well at least almost everyone, has had headaches from time to time, and we all know how miserable they can make us feel. In fact, at some point in time, 9 out of 10 Americans suffer from headaches that range between mild and dull to throbbing, intense, and debilitating, sometimes to the point of requiring bed rest in a dark, quiet room.

The common reflex is to reach for that bottle of pills and pray the headache subsides so you don’t have to call in sick and lose another day of productivity when you have so much to do. Unfortunately, between the side effects of many medications designed to help headaches and the pain associated with the headache, this approach is frequently NOT the answer. So what is?

The good news is that many studies have identified spinal manipulation therapy (SMT), the main type of care utilized by chiropractors, as being very effective for popular types of headaches—in particular tension-type headaches that arise in the neck. An important 2001 study reported that SMT provided almost immediate relief for headaches that arose in the neck with SIGNIFICANTLY fewer side effects and longer-lasting results compared with commonly prescribed medications.

Another interesting study that found similar results included tracking the prevalence/frequency of headaches after treatment stopped. The authors of the study reported the patients receiving SMT had continued to experience sustained benefits throughout the following weeks, and even months, in contrast to those in a medication treatment group where headaches came back almost immediately after they discontinued treatment.

The most commonly prescribed medication for tension-type headaches are non-steroidal anti-inflammatory drugs (NSAIDs). Common over-the-counter options include ibuprofen (Advil, Nuprin, etc.) and Aleve (Naproxen). For those who can’t take NSAIDs because of blood thinning and/or stomach-liver-kidney problems, doctors commonly prescribe acetaminophen (Tylenol), but it can be hard on the liver and kidneys, especially when taken over time.

So, what can you expect from a visit to a chiropractor for your headaches? The typical approach begins with a thorough history and examination with an emphasis of evaluating the neck and its associated function. Your doctor of chiropractic may also perform tests designed to reduce pain and some that provoke a pain response to identify the “pain generator” or cause!

Because each patient is unique, the type of care provided will be individually determined based on the findings, the patient’s age, comfort, and preference of both the provider and patient.

So, the next time you find yourself reaching for pills because of headaches, remember that there are better options! Give chiropractic a try. You’ll be GLAD you did!!!

We realize you have a choice in whom you consider for your health care provision and we sincerely appreciate your trust in choosing our service for those needs.  If you, a friend, or family member requires care for neck pain or headaches, we would be honored to render our services.